October, 2016
In Japan, “PALFIQUE™ UNIVERSAL FLOW” is sold under the name “ESTELITE UNIVERSAL FLOW™”, and “PALFIQUE™ Bond” is sold under the name “Tokuyama Bond Force™ II”.
There isn’t a single day in clinical practice when I don’t reach for flowable composite resin. Introduced roughly 20 years ago, it created a revolution in conventional composite resin restoration. For small carious lesions, restorations are often completed using flowable composite resin alone. For extensive reconstruction of crown anatomy, it is important to combine flowable and paste-type composite resins, using each where it performs best. The new ESTELITE UNIVERSAL FLOW™ has three viscosity options and seems poised to further increase the frequency at which flowable composite resin is used.
The clinical qualities required of flowable composite resin, which conventional CR paste lacks, are high wettability with the bonded surface and a viscosity that allows the material to self-adapt to target areas. This article reports on two cases where these properties were put to use by selecting the viscosity of ESTELITE UNIVERSAL FLOW™ to suit the clinical situation.
Case 1: Filling a Class I Molar Cavity (High and Super Low)
A Class I molar cavity is most susceptible to polymerization shrinkage stress owing to its high C-Factor. The key to avoiding bond failure at the cavity floor is to first apply Tokuyama Bond Force™ II, then place a very thin first increment of the highly wettable ESTELITE UNIVERSAL FLOW™ High (OPA2) onto the cavity floor to completely optimize bond between the bonding layer and the tooth structure. From the second increment onward, the low viscosity of ESTELITE UNIVERSAL FLOW™ Super Low (A2), which allows for sculpting, can also be used to directly reproduce fine occlusal anatomy.
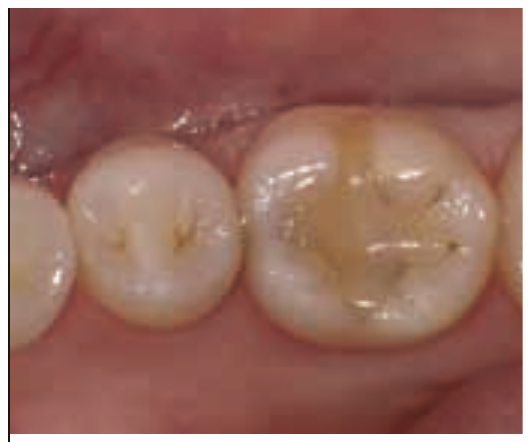
Fig. 1 #36: Re-restoration to improve the marginal fit of an existing composite resin restoration was planned for a 27-year-old female.
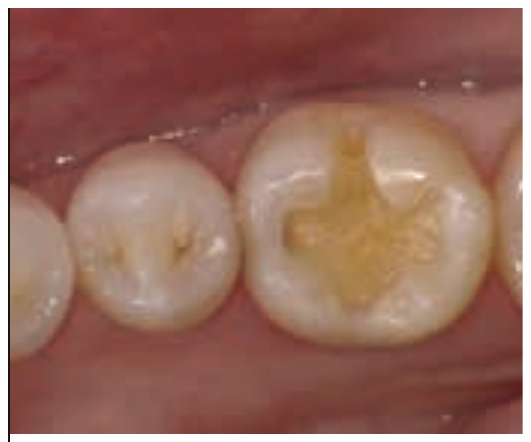
Fig. 2 Removal of the old restorative material and completion of cavity preparation.
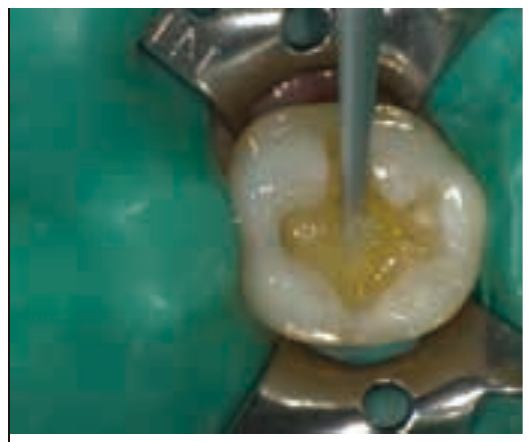
Fig. 3 Bonding agent (Tokuyama Bond Force™ II) applied, followed by light curing.
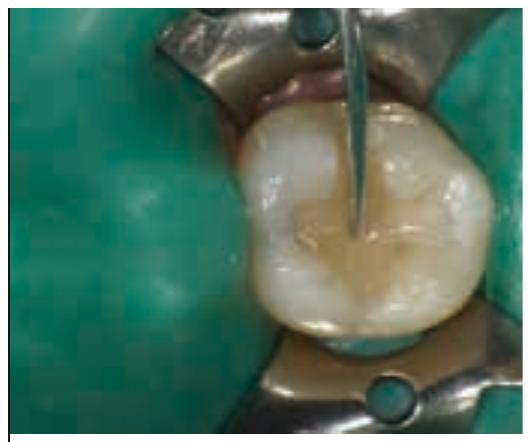
Fig. 4 First increment of the layered filling, using ESTELITE UNIVERSAL FLOW™ High (OPA2).
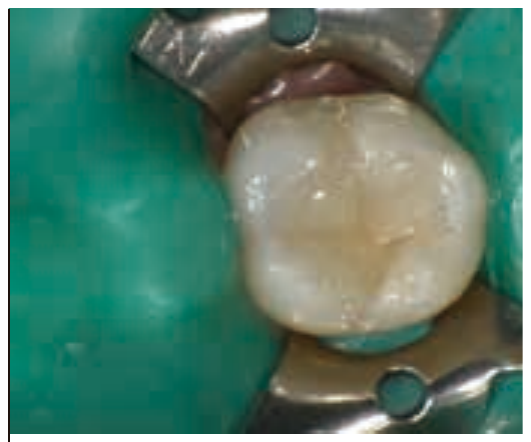
Fig. 5 Second increment of the layered filling, performed cusp by cusp using ESTELITE UNIVERSAL FLOW™ Super Low (A2).
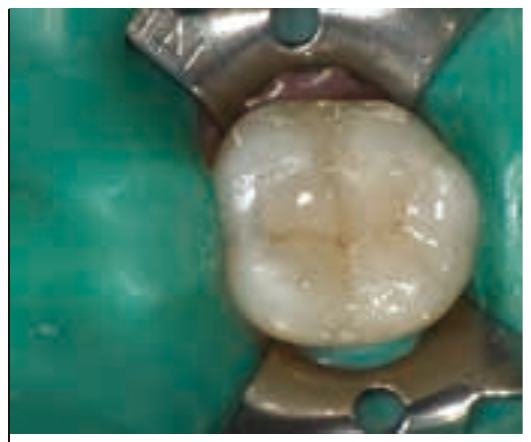
Fig. 6 Completed filling.
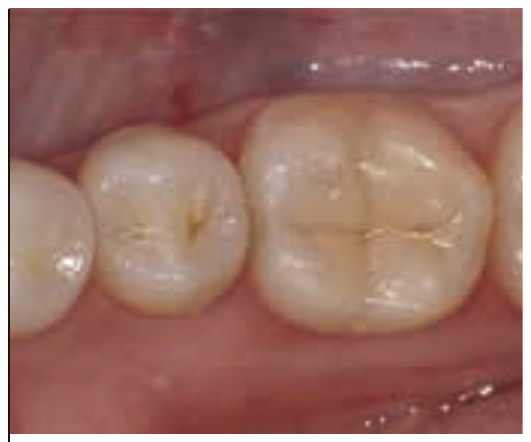
Fig. 7 Postoperative.
Case 2: Filling a Narrow Space at a Fractured Anterior Tooth and Diastema (High and Medium)
When seeking esthetic improvements for a fractured anterior margin and diastema, combining a flowable composite resin with a 3D Clear Matrix proves extremely effective. Restorative filling begins after etching of the unprepared enamel surface with phosphoric acid and applying Tokuyama Bond Force™ II bonding agent. Filling of the narrow cervical space between the matrix and tooth structure starts with ESTELITE UNIVERSAL FLOW™ High (OPA2), since it reaches fine detail extremely well. Meanwhile, at the incisal edge, ESTELITE UNIVERSAL FLOW™ Medium (CE) can be used to reproduce depth and translucency because it can be sculpted and comes in a wide range of shades.
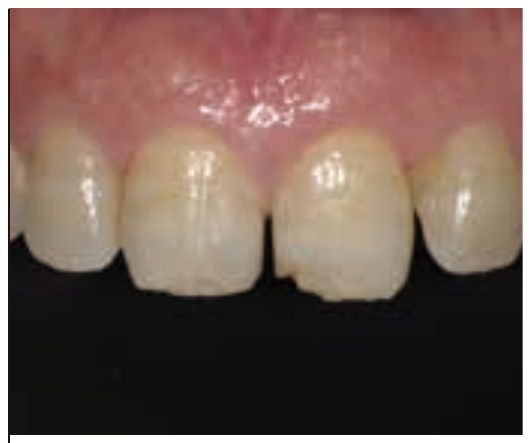
Fig. 1 Preoperative: The chief complaint was esthetic dissatisfaction caused by a fractured anterior tooth and diastema in a 55-year-old female.
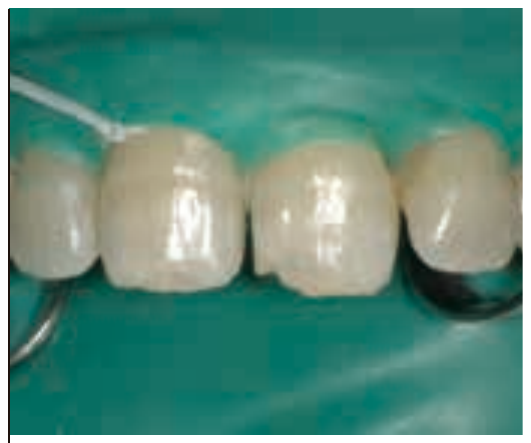
Fig. 2 The diastema measures approximately 1.0 mm. An indicating closure of the diastema with composite resin.
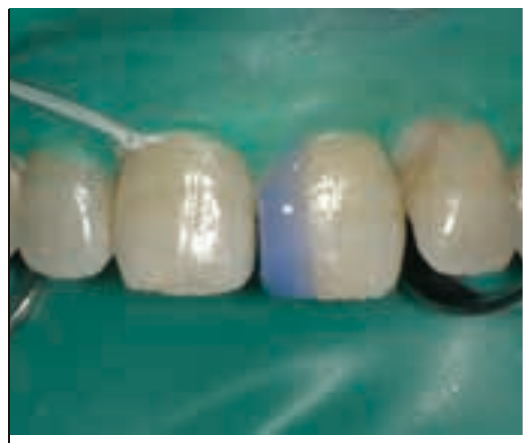
Fig. 3 Application of phosphoric acid etch.
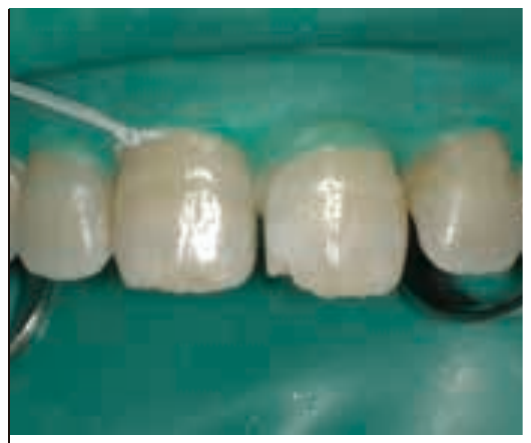
Fig. 4 Rinsing and drying.
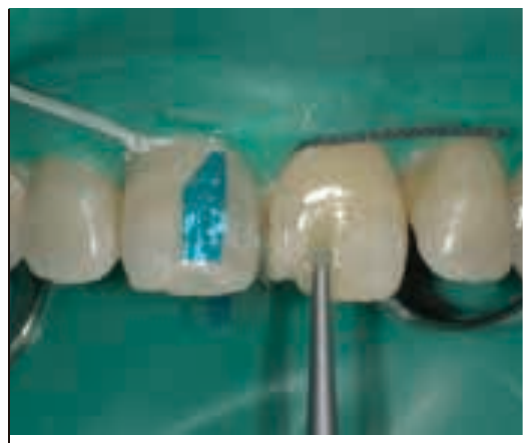
Fig. 5 Application of bonding agent (Tokuyama Bond Force™ II) a, followed by light curing.
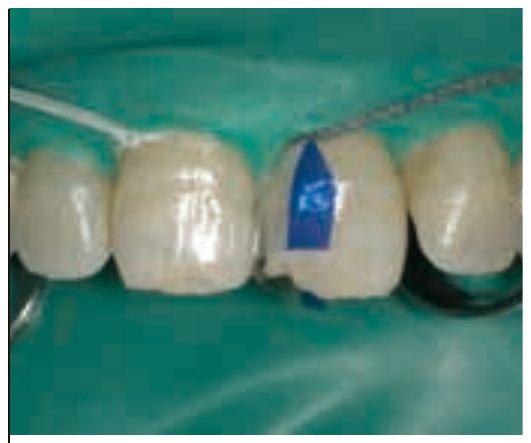
Fig. 6 Try-in of the 3D Clear Matrix.
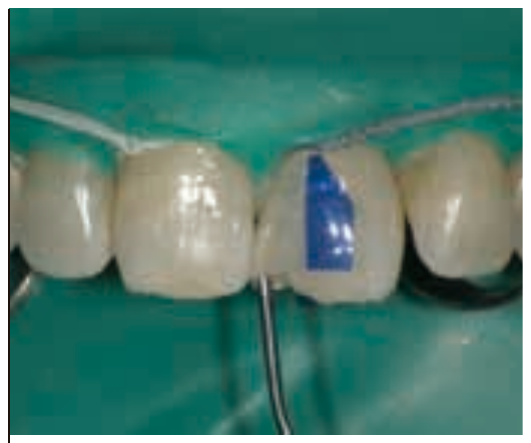
Fig. 7 Filling the narrow space near the cervical margin using ESTELITE UNIVERSAL FLOW™ High (OPA2).
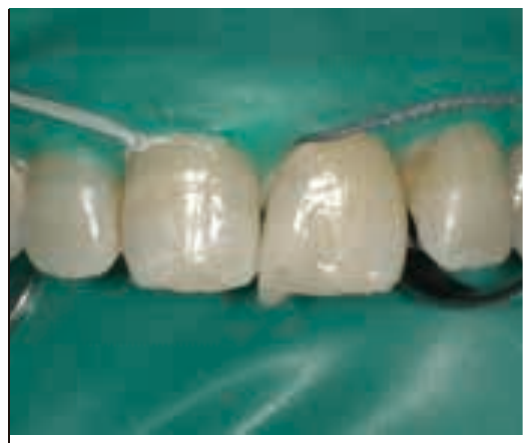
Fig. 8 Filling at the incisal edge using ESTELITE UNIVERSAL FLOW™ Medium (CE).
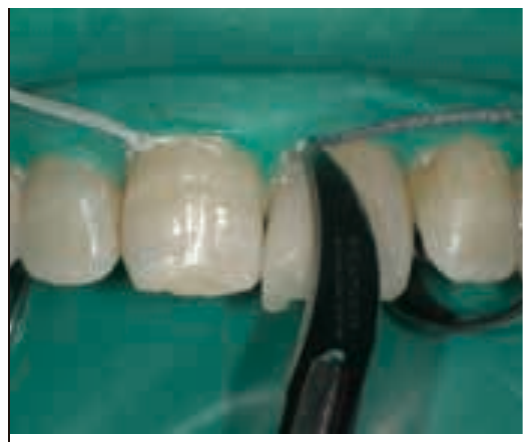
Fig. 9 Trimming of excess composite resin at the cervical margin.
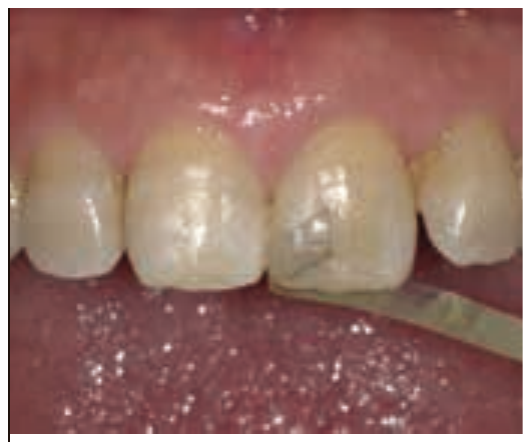
Fig. 10 Contouring of the incisal corner.
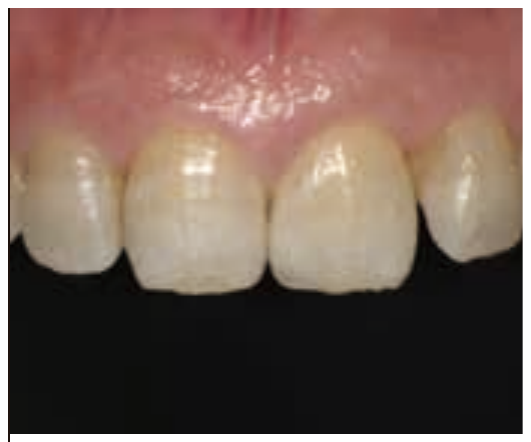
Fig. 11 Postoperative.